
October 2022
My day today consists of 1. research writing and reading for the last chapter of Paper Thin; 2. Email blitz! 3. an ultrasound-guided deep steroid injection in my hip and neck to alleviate some of the pain and inflammation; 4. More kidney blood tests (& associated worry).
More on the Adele / mature student angle here, with a mention for @BirkbeckUoL!
https://www.theguardian.com/education/2022/oct/30/adele-academic-mature-students-career-break-study
Catching up on some admin work while jamming to the latest postal arrival. A very nice pressing of Franz Matthews and Local Suicide's Tutan Jamon on clear vinyl!

A brief thread on rheumatoid arthritis prompted by another terrible article about it in The Times. This illness is so badly understood in the general population. People hear "arthritis" and imagine a mild osteoarthritis "like my granny had".
The first thing to say is: osteoarthritis is also awful. Disabling, painful, and NOT to be trivialised. That this condition is seen as an affliction of seniority and therefore not given due seriousness is very wrong.
Rheumatoid arthritis is, instead, an autoimmune disease in which the body's own immune system attacks the joints *and other internal organs*. It is treated with heavy immunosuppression. Osteoarthritis, on the other hand, is caused by "wear and tear" on the joints.
None of these things occurred to me when they first told me I had "arthritis". I should say also that just the joint pain is bleaker than I can describe to someone who hasn't had it.
As followers may know, as a result of RA and its treatment I've had a stroke, several pneumonias, vasculitis and nerve damage, sepsis, norovirus, and now BK Virus and severe kidney damage. I developed secondary immunodeficiency.
However, it's also really problematic when rheumatoid and reactive arthritises are conflated with mild osteoarthritis. The consequences of how we have to treat RA, on top of the disease itself, are really serious.
Sorry for a crude analogy, but one the blokes will get: the pain of standing on a swollen arthritic foot/ankle, for instance, is, in my view, equivalent to being kicked in the testicles on each step. Every step comes with that wave of dire nausea.
I hate this kind of article because it reinforces a popular perception that these conditions are somehow the fault of the sufferers.
As though if I'd eaten a few more oily fish and nuts I wouldn't have developed the disease that has wrecked my entire life.
So when I saw an article today in The Times headed "Arthritis: Six Ways to Protect Yourself" I immediately predicted it would be nonsense. And it was. It's full of "tips" like "eat oily fish and nuts".
It also totally trivialises it. I mean, how serious can a condition really be if you can "protect" against it by eating a few more seeds and nuts?
Anyway, I'll stop ranting here. But I remember writing to a newspaper saying exactly this, about 15 years ago, responding to a near identical article. It's a grave shame that, almost two decades later, the coverage of these devastating conditions has barely improved.
There's one thing they recommend that probably would help: giving up smoking. Almost the only consistent risk factor apart from being female. But this is just generic health advice.
The Register covers the death of Kathleen Booth, the inventor of assembly language while at @BirkbeckUoL
https://www.theregister.com/2022/10/29/kathleen_booth_obit/
"Yep, it's definitely computer code" https://x.com/wesbos/status/1586098245910003712
Spoke with kidney clinic. Virus activity & kidney function are worse. If decline continues at this rate, it looks like failure by Christmas. But they are hoping to see an improvement in the next fortnight. If not, it's more of the high-dose IVIG, which makes you feel awful.
So I just have to keep my fingers crossed that the IVIG can clear it out. Perhaps it will and this will all just become a hypothetical nightmare that never was. Decline also might not be linear. So many unknowns. As the doc put it: "we're in an 'evidence-free zone'". Great.
But it's very hard not to worry, waiting on blood tests that may show rescue and salvation, or just the next step in a not-very-pleasing, lethal graphic trajectory. It doesn't help, either, that I feel so terrible with the arthritis meds withdrawn.
"Is Rishi Sunak the right man for ultra-volatile pseudo-monetary systems that benefit a technocratic elite at the expense of everyone else on the planet?"
Well, he's in charge of the UK £, so he's got form.

All those scholars outraged at the corporate takeover of Twitter, threatening to withdraw, you're gonna love it when you hear about the mass for-profit corporate ownership of academic publishing platforms.
Nose-picking primates spark scientific quest 🤔
https://www.bbc.com/news/science-environment-63349621
Adele to take a break for English literature degree
https://www.thetimes.co.uk/article/adele-to-take-a-break-for-english-literature-degree-x3zdvl2sp
Linus Torvalds bids 486 Linux adieu
https://www.zdnet.com/article/linus-torvalds-bids-486-linux-adieu/
Out today!
Eve, Martin Paul (2022) Open Access in the Humanities Disciplines. In: O'Sullivan, James (ed.) The Bloomsbury Handbook of Digital Humanities. London: Bloomsbury, pp. 223-231.
https://eprints.bbk.ac.uk/id/eprint/40856/
VoR free to download, though not openly licensed. Thanks to Bloomsbury for removing the embargo!
whoops. It's "Handbook to the Digital Humanities" not "of". Now corrected in metadata record.
Channel 5 National News covered our #forgotten500k vigil today for Evusheld. Their report features my face on a placard!
https://m.youtube.com/watch?v=ylglsI4nULg&feature=share
Irked that I will not be able to attend the @CrossrefOrg annual meeting this afternoon. I hadn't foreseen the hospital calling me in today and, although I am now home, I am wrecked after the IVIG.
Came home to this "fierce" little chap pretending to guard the front door!
I like to think he was waiting for me to return from the hospital. In reality, he probably walked this way, got tired where he was, and decided to kip there.

The whole experience of organizing a protest, then not being able to attend, is emblematic of this whole thing. I am living it vicariously online because the UK government has chosen not to protect the #Forgotten500k people in my position.

Thanks to Lord Mendelsohn for attending the vigil today! #Forgotten500k

Thanks to @CatherineWest1 for coming to the vigil to signal her support for the #forgotten500k and the Evusheld scandal.

Great to see @libdemdaisy and @drlennardlee join the vigil outside Parliament Square for the #forgotten500k. No sign of the new health secretary, @SteveBarclay, yet.

We have organised a vigil, taking place right now, in Parliament Square for the #forgotten500k. I have two friends representing me as I approach 1,000 days of shielding. Most of our patients cannot attend in person. @SteveBarclay, back in post, could fix this with Evusheld.
I appreciate that nobody ever wanted so large a picture of my head...
The vigil gathers. Politicians inside need to stop blathering about the circus of Westminster and instead address this real issue, affecting people's actual lives.
(I should say: the logistics of organising an event like this in Parliament Square are *absurd*. You have to designate wardens, get liability insurance, have a dedicated site manager etc. A nightmare. @MarkOak04974342 and @NikolaBrigden did so much to make this work!)



Pleased to have been able to feed into this report.
Operationalising Open Research Europe as a collective publishing enterprise - Publications Office of the EU
https://op.europa.eu/en/publication-detail/-/publication/81b9cd30-5104-11ed-92ed-01aa75ed71a1/language-en
Not actually quite right for OLH. We left Ubiquity 100% several years ago. Our primary concern was buyout - and then having our infrastructure controlled - by a major for-profit publisher. https://x.com/punctum_books/status/1584919493314314242
From day zero, everything I have ever said about open access has centred on this: the for-profit APC model won't save us.
In OA and the Humanities: "it is clear that this is a seriously flawed model". 1/1 https://t.co/Dd1sTyYOEL
Then, following arXiv and KU, which was not for profit at the time, we built @openlibhums to show what might work instead. 2/2
It's great for patients to have all their blood test results at the hospital available via an app. Except when they show something terrible and you have several days to wait before you speak with the consultant.
They say "ignorance is bliss" and they may be right.
Here I am in The Times, quoted alongside @SGriffin_Lab and others.

Well, here I am and ready to go. It's an "exceptional/urgent circumstance" so I'm the only patient on the infusion ward, which isn't usually used on Mondays. Think I'm going to be flushed full of about £7k of immunoglobulins today.

Off to bed nice and early for a 5am start tomorrow. This is the beginning of the serious treatment phase. With any luck, this will get this virus out, my kidneys working, and my tweets can go back to obscure stuff about scholcomms metadata, programming languages, and lit studies.
"I spurn your comfortable and very expensive bedding"


The question is: can I sneak this into my hospital bag?

I was just looking at the RAPID C-19 report on Evusheld.
They say "we need more trials". They also say "we can't get the trial data we want". Why? There aren't enough "events". Meaning: "we can't infect enough vulnerable patients to see how many die".
Incredible.
Alright, let's put aside the fact that this makes me want to puke - "drat, we can't infect enough vulnerable people to get the data!" - this is "demand the impossible" territory.
We won't auth this without further trials.
But further trials are not possible anyway.

How the heck can whoever the DHSC asked for advice be credible given this? The lead AUTHOR of the piece they cite says they put out "the opposite of what the article reported".
It's a scandal.
@libdemdaisy @andrewgwynnemp @APPG_VGP https://x.com/martin_eve/status/1584146191616352256
Incredible.
@DHSCgovuk, @RobertJenrick & @theresecoffey replied to us citing an academic article from the US against Evusheld.
The Prof who wrote it: ‘The UK Government used our study as evidence that more trials were needed, but that’s the opposite of what we reported’.
Well, OK, wow. The Mail on Sunday and @EnnalsEthan has taken on our #Forgotten500k Evusheld campaign. This is NOT a partisan political issue; it's a political no-brainer. @RobertJenrick @theresecoffey
https://www.dailymail.co.uk/health/article-11343551/Calls-grow-health-chiefs-anti-Covid-drug-Evusheld-green-light-protect-vulnerable.html
Quite jaw-dropping exposure of @DHSCgovuk, @RobertJenrick @theresecoffey on Evusheld:
‘The UK Government used our study as evidence that more trials were needed, but that’s the opposite of what we reported,’ says Prof Adit Ginde at the University of Colorado.
Then, amazingly, Tory grandee Lord Lansley wades in(!) Hope you are listening @RobertJenrick @theresecoffey -- this is your OWN PARTY:
"Not a single doctor I have spoken to believes that there is any merit to further delay or deliberation – in fact, quite the opposite."
Who else?
‘This is a very bad decision by the British Government,’ says Dr @YannNgyn, a clinical medicine expert at the University of Paris who ran an observational study involving more than 1,000 Evusheld patients.
We agree. In fact, @drlennardlee found 125 clinicians from 17 clinical areas, across all 4 nations, who all agreed: we need Evusheld now. https://getevusheld.uk/assets/downloads/consensusstatement.pdf
"I am on my 951st day of shielding"
"My eldest daughter I haven't held or cuddled since this began"
"On Monday morning, my daughter woke up with Covid-like symptoms, which meant I had to isolate from the family, living in the summerhouse again."
https://www.youtube.com/watch?v=Vs623byoC3c https://x.com/martin_eve/status/1583845846088458241
I know I am probably alienating a huge number of my followers by promoting the Evusheld scandal so much. But it's so important for 500k people at the moment.
What are their (our) lives like and why do I care? PLEASE take 4 minutes to watch this and RT.
https://youtu.be/Vs623byoC3c
This lack of leadership is actually killing people. We can't get a minister just to step in and fix the Evusheld mess for precisely this reason. They seem to care much more for their own infighting and power jostling than people's lives. #forgotten500k https://x.com/lewis_goodall/status/1583486336840781824
It's been MONTHS. We've had campaigns all lined up and ready to go.
Then the whole government changes.
Some new person with no experience in health is suddenly put in charge and doesn't get the issue.
So we write and lobby and push the issue. Eventually, they see what a fiasco it is and that it is something that needs handling and not a fringe issue. We feel we're getting somewhere, then... Boom. Another government shutdown / total change.
Sometimes the Ministers have been SO cowardly, like Steve Barclay, seeing the scale of the cock up, that they wait until the actual day they are leaving to reply to us. Having sat on it for 8 weeks. It's contemptuous of the public.
The Con MP who was ranting about representatives who act in their own, rather than the public, interest was right. If you're not going to be in the job for long, it's "keep your powder dry and don't ask for any more money for public services".
https://www.bbc.co.uk/news/av/uk-politics-63320605
These MPs seem to think "I'm only going to hold this ministerial position for a matter of weeks. I don't want the Party to think that the only thing I did in that role was spend more taxpayer money. It will jeopardise my career."
And people are suffering and dying, every day.
Is that too extreme? No.
"Approximately 25% of immunocompromised patients who were admitted with Covid died in hospital"
"Immunocompromised patients remain at elevated risk of death from COVID-19"
https://doi.org/10.1101/2022.08.08.22278576
Too extreme? People aren't dying as a result of ministerial inaction? Yes, they are.
Kidney transplant patients have 6x greater risk of death and women
with Down's Syndrome have 10x greater risk of death from Covid.
https://doi.org/10.1101/2022.08.13.22278733
So what should we do?
@LanceTurtle's recent paper said "Targeted measures such as [...] monoclonal antibodies should be considered for this group."
That's Evusheld at the moment.
UK gov: tumbleweed.
"Sorry, there's nobody here to take your call. We're too busy infighting."
They keep arguing that we need more testing against Omicron.
But it's just an excuse. The recent paper from the Crick Institute in The Lancet said "Evusheld .... showed strong neutralisation against all omicron variants tested".
https://www.thelancet.com/journals/lancet/article/PIIS0140-6736(22)01938-9/fulltext
Another real world study from University of Arizona also countered the total nonsense from the UK's DHSC about lab based data trumping real world studies. https://doi.org/10.1016/j.amjmed.2022.08.019
"While a recent in-vitro study showed
reduced antibody neutralization of Tix-Cil [Evusheld] against Omicron variants, this did not have a significant clinical outcome in our study or similar studies during the Omicron variant period".
So the excuses pile up. But it basically boils down to this: the current leadership void is a BLACK HOLE. No minister has the guts to step in and fix this Evusheld mess created by their own party's internal spats.
The Evusheld mess could be fixed by @RobertJenrick with just a word. But he's got to care more about people dying than the internal soap opera of his party right now. It's not clear that he does, or any of them do.
So I say again: this leadership contest is killing people.
Today's little Rust learning experiment. Recreated the GNU "cat" (concatenation) tool https://github.com/MartinPaulEve/catr
Re-reading @lawsonstu, ‘The Political Histories of UK Public Libraries and Access to Knowledge’, in Reassembling Scholarly Communications: Histories, Infrastructures, and Global Politics of Open Access, ed. by @martin_eve and @jwyg (Cambridge, MA: MIT Press, 2020), pp. 161–72
It's OA here: https://direct.mit.edu/books/book/4933/Reassembling-Scholarly-CommunicationsHistories
I really love this chapter and the way it charts the contradictions of liberal education reform -- and the role of the library -- in both class and imperialist contexts.
It put me on to so much great stuff. More than I can type into tweets (in alt text!), but this footnote on colonialism and libraries.

In hospital next week so today's a flexi work day. It's some book writing/research, then some COPIM project infrastructure stuff, then teaching myself some more Rust. Optimistically I want to put some playtime on the synthesizers in there at the end...
Wahey! Done 1,000 good words of book before 7am! Impossible things before breakfast...
Here we go. I'm all setup for 3 days of high-dose intravenous immunoglobulin next week from Monday to Wednesday. BK Virus is about to get a bashing! Here's hoping for kidney improvement.
Also, it ain't £1k. You'll pay ~£500 for a private consultation/prescription, then the pharmacy will put a markup on the drug, then you'll pay approx £200 for administration. Closer to £2k. https://t.co/5K0lt5s0Uz
Government could have bought doses for a fraction of this.
Here I am talking about the challenges of only seeing people who have been able to isolate, 950 days later. Going through this all over again now, trying to see my brother and my baby nieces, before I miss their entire childhood. #Forgotten500k https://podcast.crisiswhatcrisis.com/forgotten500k
https://x.com/ArchbishopSarah/status/1583148896767070208

One member of the household has insomnia. Another does not.

Seriously, for 6 months now:
* Extended Con Leadership Contest
* Political Recess
* Conference Season
* Death of the Queen
* New Prime Minister
* Fresh Con Leadership Contest 1 month later
If you need something new done in UK government, there is nobody there to do it. https://x.com/martin_eve/status/1583136073613312005
Day 4 #Forgotten500k #Evusheld


‘UK Government Privatises Covid Response and Forces Vulnerable Immunocompromised Patients to Pay for Covid Drugs’ - a press release from @evusheld4theuk
@EnnalsEthan @BBCFergusWalsh @TomChivers
https://getevusheld.uk/assets/downloads/2022-10-20-Private-Provision-Press-Release.pdf
This actually has far-reaching consequences for our ongoing pandemic response. It's a change of policy in a dangerous way. Great comment also, here, from @drlennardlee

While @RobertJenrick meets MPs to try to justify the terrible DHSC decision, we're sharing Lesley's story as part of the #Forgotten500K campaign. Like many of our patients she has been shielding for almost 3 years now. Evusheld could give her some safety.
https://www.youtube.com/watch?v=lQGHOjKf2xQ&t=1s
It's Day Four of our #Forgotten500k campaign for Evusheld on the NHS. Here's a recap, featuring music by me :P
Well I'm 5 days into the withdrawal of Baricitinib, my primary biological immunosuppression, as we try to combat the kidney virus. I can feel the painful fluid accumulating in my shoulders, neck, wrists, hands, knees, and feet as the rheumatoid arthritis kicks in.
At this point, a revolting nausea now pangs through my body with every burning step as the arthritis kicks up in my feet, ankles, knees, and hip. Hands hurt but tolerable for now. Still waiting to begin the high-dose IVIG. Distracting myself with work and the Evusheld campaign.
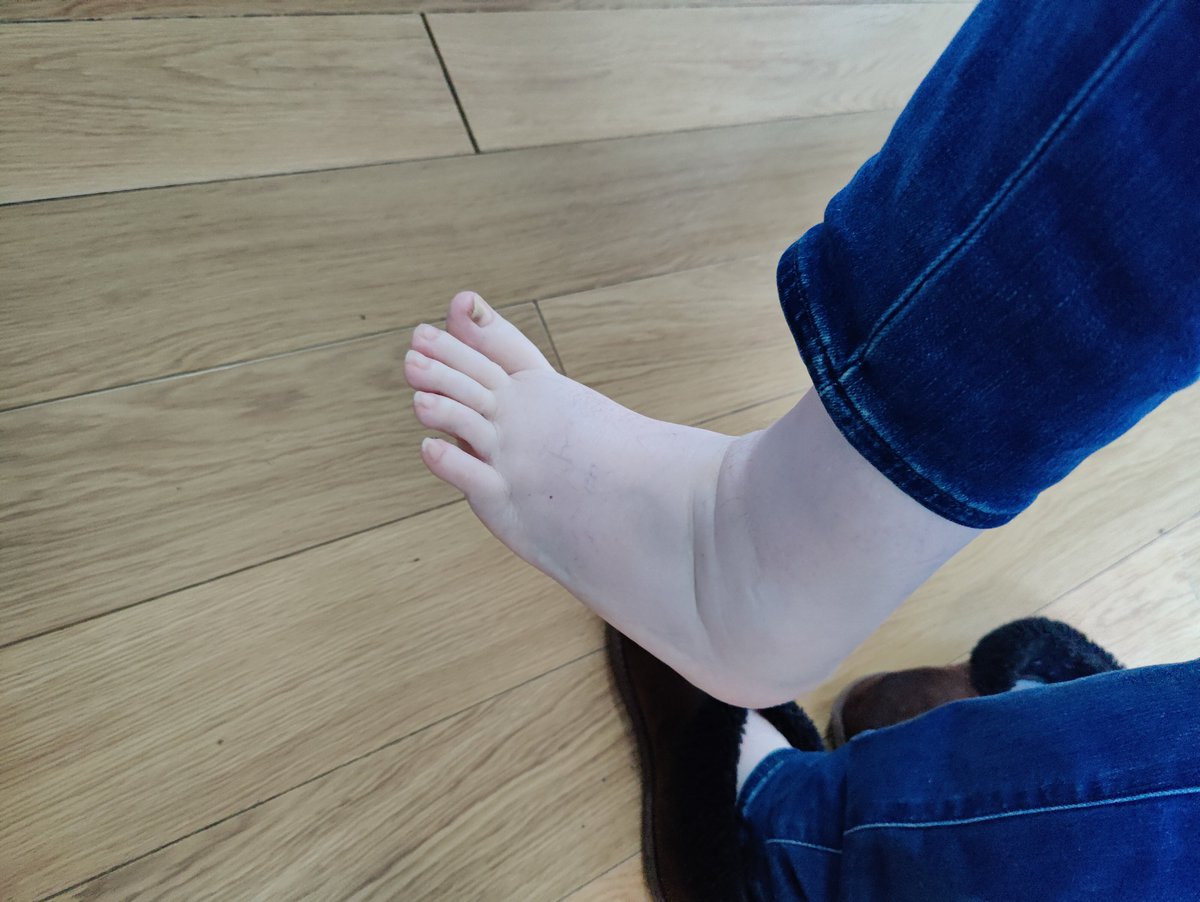
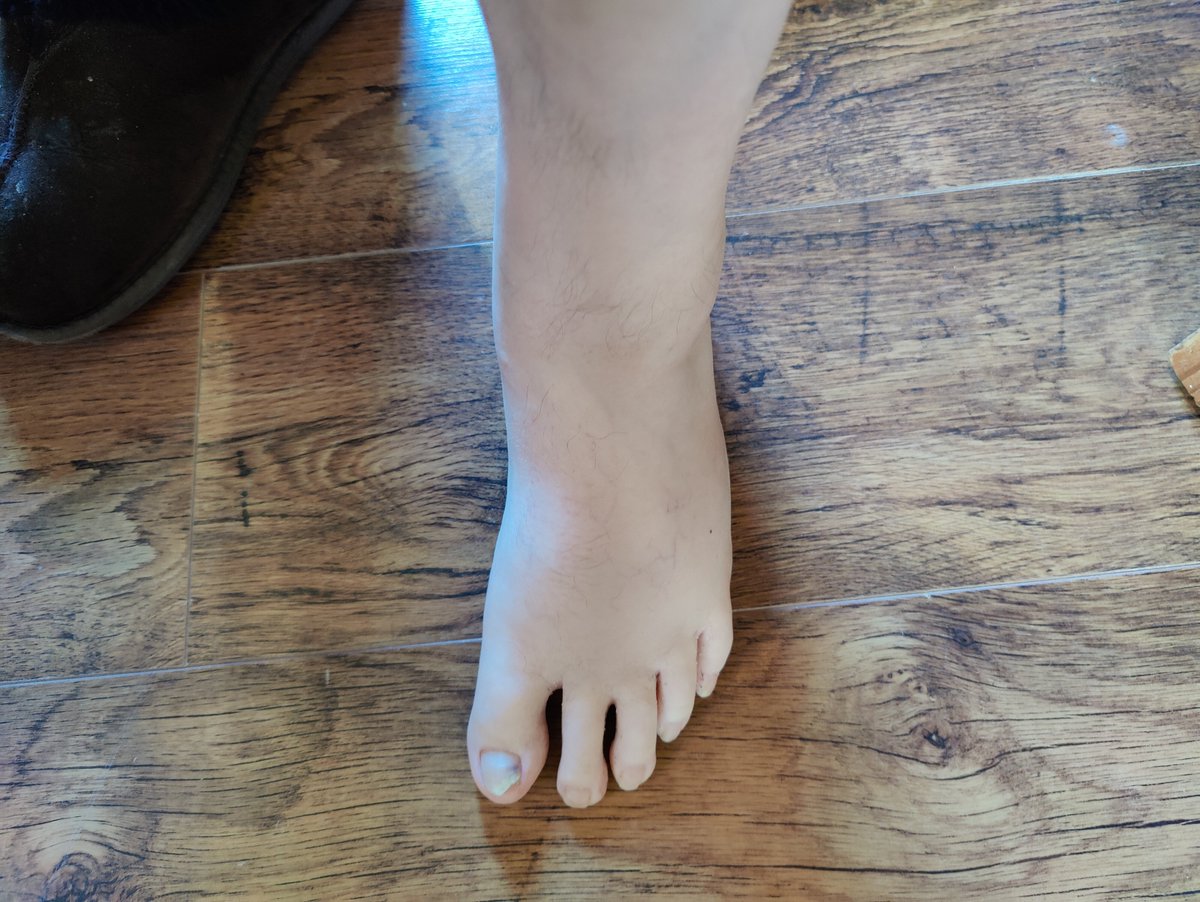
Probably "too much information" but here's what a foot with rheumatoid arthritis looks like after just a short while w/out the meds. Joint invisible b/c there's so much inflammation. Hot and swollen. Oh. And it hurts. A lot.
This is, of course, just me publicly logging what it's like as my rheumatoid arthritis becomes uncontrolled with the removal of immunosuppression to clear the virus that's attacking my kidneys.
Last night was terrible. Arthritis flared so badly and painfully that I just burst into tears several times. Incredible pain all over and feverish sensations with nausea. Needed help getting changed for bed as couldn't do it myself. Awful. Much better this AM thankfully.
Love a bit of evening talk recording and captioning...
It is so wrong that only those with wealth can have health. Goes against a basic principle of our healthcare system. I am already fielding absolutely desperate emails from people in tears who can't afford Evusheld privately. #Forgotten500k
AstraZeneca has just announced the private availability of Evusheld in the UK. While we recognise that this will allow some people to access the drug, we are of course disappointed that it has come to this. 1/4
We now have desperate members scrambling to find out how to get it with others saying they can't afford it. Others are preparing to take out new credit cards. In the middle of a cost of living crisis, vulnerable people have been abandoned by @theresecoffey and @RobertJenrick 4/4
This includes roll out to all vulnerable people who are less likely to have mounted a response to vaccination”. We continue to believe that the only equitable route is via full NHS availability, free at the point of use. 3/4
Our campaign is unchanged by this development. As we have stated from the outset, we exist for one purpose: “to get this drug introduced in the UK with access for all those who need it. 2/4
Also today: our ad van is patrolling Westminster for the #forgotten500k Evusheld campaign!
@RobertJenrick @theresecoffey @DHSCgovuk
Obviously, I had to get someone to take the photo on my behalf, as I'm still shielding, in isolation.


We’d like to invite you to join us, tomorrow, Thursday 20th October, 1-2pm, online, for a special discussion hosted by Tortoise Media about the Government's refusal to make Evusheld available on the NHS!
The link to tune in is here: https://tortoisemedia.zoom.us/j/87035767579
The panel includes Lord Mendelsohn; @libdemdaisy MP; @drlennardlee, Academic Clinical Lecturer in Medical Oncology at the University of Oxford; @MarkOak04974342, Evusheld for the UK, and @rowntron, Director of Research, Services and Engagement at Blood Cancer UK.
@evusheld4theuk
Thanks so much to Tortoise for hosting this!

BBC Radio 4 Inside Health ran a substantial segment yesterday featuring our member, Shannon, and a discussion of Evusheld and the #Forgotten500k. https://www.bbc.co.uk/sounds/play/m001d5jf
Thank you SO MUCH to @ShannonB for sharing her story. We'll have more on this next week. It takes a lot of bravery to step forward and speak about this.
Today our massive national press ads for the #forgotten500k who need Evusheld are in The Times and The Daily Mail.
@RobertJenrick and @theresecoffey could fix this and help to free NHS bed space by protecting the immunocompromised. It's not hard.

Today's Research* playbook draws attention to the Office for Students and a report that shows their lack of "a model that could understand, systematically, the combined effects of the various financial pressures on the sector as a whole and on individual institutions". 1/1
What a surprise that the OfS knows virtually nothing about the finances of the sector that it regulates. 2/3
There is nothing good about the OfS. 3/3
Today we're launching the first of our #Forgotten500k patient stories.
Mark has been shielding for over 900 days. He fears he will never see his 90-year-old mother again. He has to isolate and sleep in the summerhouse so his child can attend school.
https://youtu.be/L9NuCp29UXM
There's an obvious answer to this. Evusheld would make Mark's life so much safer.
My three weeks in hospital in September left me extremely weak. It's frightening how quickly you lose muscle and any fitness. I'm taking breaks for recovery walks every day but it's slow going. It's likely also to be disrupted when the rheumatoid arthritis meds phase out.
So annoying to think I might just get back to some level of activity... Only to have all my joints explode in a cacophony of searing pain. Still, there's nothing to do but try. And hopefully withdrawal from immunosuppression will help clear the virus.
Toby interlude

Authors’ names have ‘astonishing’ influence on peer reviewers
https://www.nature.com/articles/d41586-022-03256-9#ref-CR1
A really great talk from @drlennardlee about leadership, protecting the most vulnerable, and the #forgotten500k in the UK.
https://www.youtube.com/watch?v=Z6FFAqQr6TQ&t=50s
A friend sent me this canny underlining. If only there were some other term for a unit that provides warmth that permeates the entire building.


It's not a surprise, but @academia (dot edu) makes it very hard to unsubscribe from their unsolicited emails. I don't have an account with them as far as I know. But the unsubscribe button asks me to sign in.
Today's full-page #forgotten500k ad is in The Daily Telegraph. This is not a party political issue. Newspapers across the entire political spectrum have given us space because they can't quite believe the extent of the Evusheld scandal. @RobertJenrick @theresecoffey @DHSCgovuk

Time is ‘running out’, @RobertJenrick, to protect the #forgotten500k from Covid this winter amid calls for ‘life-changing drug’ https://www.thescottishsun.co.uk/health/9621596/time-running-out-protect-thousands-covid-life-changing-drug/
Research* Playbook today hits the nail on the head today -- and it's bleak. UK HE funding is now in a catastrophic death spiral with no relief possible or planned. 1/4
"With inflation predicted to exceed 10 per cent this month, the student loan repayment threshold is already plummeting in real terms, just as the value of the undergraduate tuition fee is withering on the vine." 2/4
The next few years will see the Russell Group over-recruiting students just to stay afloat, while the student experience worsens, and other institutions will go bankrupt. 4/4
"We are quickly approaching the point, if we are not there already, at which universities in England cannot afford to teach English undergraduates." 3/4
Today begins the final push on the writing of Paper Thin. It looks as though more of the last chapter of this will be written on hospital wards than I anticipated, but I'm feeling excited about the writing endgame.
It's also Day 2 of our Evusheld #forgotten500k campaign. There are more national newspaper ads today and I'll be sharing some of the, quite frankly tragic, stories behind this.
Then I've got some meetings with PhD students. Hoping I can help them also to feel enthusiasm for their projects - the summer break can prove a motivational challenge.
"cryptoasset education"

(My nickname at home is, actually, Mouse...)

Here's the all-party parliamentary group (APPG) for groups vulnerable to pandemics encouraging all MPs to attend the meeting with @RobertJenrick later this week. Please do encourage your MP to go.
https://appg-vulnerablegroups.org/news/post/minister-of-state-for-health-robert-jenrick-to-meet-mps-and-experts-regarding-access-to-evusheld
Huffington Post on the case today, too https://www.huffingtonpost.co.uk/entry/campaigners-call-for-evusheld-covid-drug_uk_634d2dc4e4b08e0e60857ca8?xz
The @DHSCgovuk are so frustrating.
“To increase the evidence base upon which Evusheld can be assessed, we are urgently exploring commissioning a clinical trial”.
NO. You cannot do an RCT unless there is true uncertainty around the trial arm. 🧵 1/15
https://bmcmedethics.biomedcentral.com/articles/10.1186/s12910-021-00712-5
In this case, they are claiming that there is uncertainty about the efficacy against Omicron due to lab-based testing showing reduced neutralisation. They want a trial with placebo.
Yet Al-Obaidi et al. from the University of Arizona say different 2/15
https://doi.org/10.1016/j.amjmed.2022.08.019
I've used this analogy before (borrowed from @drlennardlee): we have some parachutes that appear to work 80%-90% of the time in real-world situations. The DHSC want to test this by getting people to jump out of a plane -- but only 50% of them will get a parachute. 4/15
"While a recent in-vitro study showed reduced antibody neutralization of [Evusheld] against Omicron variants, this did not have a significant clinical outcome in our study or similar studies during the Omicron period" 3/15
It's the only way to be sure they're working, of course! </sarcasm>
5/15
We further ran a poll of our patient group. 86% of them said that, with a randomised control trial to placebo, they would have to continue shielding. So you're going to get totally skewed data anyway. 6/15
But the basic message from patients here was really clear: WE ARE NOT GUINEA PIGS FOR YOUR DATA CERTAINTY.
Real-world data show that Evusheld works. In the RCTs, people who got the placebo died in much greater numbers than the Evusheld arm.
A TRIAL IS NOW UNETHICAL.
7/15
Has @DHSCgovuk actually considered that the reason the trial they want hasn't been run is because... it's not ethically possible? 8/15
The other thing they are obsessed with is antibody testing. This drives me round the bend. We don't know how to appraise what level of serum antibody corresponds to actual immunity. So this would need to be studied first, introducing ANOTHER massive delay. 9/15
Then, even worse, the LOGISTICS of making someone do an antibody test, waiting, getting the results, calling them back etc. will make the administration of Evusheld a nightmare*.
* metaphorically pictured 10/15
This would be fast, easy, and comprehensive. But DHSC appears SO, SO concerned that nobody who isn't totally highest risk should end up with Evusheld, that they are willing to delay until they've done the antibody studies, thereby also wrecking the ease of administration. 12/15
Instead, it would be better to rely on the cohort already identified in the NHS England RAPID-C19. 2022. ‘Defining the Highest-Risk Clinical Subgroups upon Community Infection with SARS-CoV-2 When Considering the Use of Neutralising Monoclonal Antibodies (NMABs)’ from May. 11/15
Antibody testing may also deter some patients, particularly those from backgrounds who have been shown to exhibit healthcare hesitancy. 13/15
So this is basically a complete head-desk. There's an easy win to protect these patients, but DHSC seems to want to snatch defeat from the jaws of victory. They've got an easy-to-administer, shown-to-work med. They want to make it harder to administer and have an RCT. 14/15
We have told them, explicitly, that patients will not accept an RCT. They nodded and seemed to get it. Then they issue statements to the press that they want a new trial. So frustrating. 15/15







If you want to learn about the Evusheld situation, hear what life is like for those who must continue to shield, or just want the amusement of me being interviewed by Andy Coulson, check out the "Crisis, What Crisis?" podcast. Featuring @drlennardlee & me. https://www.crisiswhatcrisis.com/podcasts/britains-lockdown-shame-the-story-of-the-forgotten-500k/
That image does make it look a bit as though @drlennardlee and I are starring in some new buddy film. "The Long Road to Evusheld".

Campaign launches for ‘forgotten’ Covid families - The Media Leader
https://the-media-leader.com/agencies-and-media-owners-back-campaign-for-forgotten-covid-families/
I raised this in my dept two years ago. The arson of HE in the UK meant that it didn't even get an agenda item at department meeting. It's not being discussed because the impending mass closure of university English depts in the UK, obviously, takes precedence. But it's major. https://x.com/Ted_Underwood/status/1581752438855327744
A side remark on trying to lobby government at this time. It's chaos. No working government for 6 months+. It's hard to lobby a government that doesn't exist. Perhaps the real libertarian experiment wasn't Truss's tax cuts, but just setting the country adrift. 1/2
It might be nice to think that this means that no/less damage was done by an otherwise damaging administration, but we can't get good things done, either. 2/2
Me in The Times (p 2) today:
“The clinically vulnerable of the UK were promised protection. Instead, they have been abandoned and forgotten.
“While the rest of the world takes care of its immunocompromised using Evusheld, the UK delays without delivering. 1/2 @RobertJenrick
“Our members lead intolerably restricted lives, will suffer the mental health effects of 1,000 days of isolation for years to come, and are dying at much higher rates than the general population with Covid-19.” https://www.thetimes.co.uk/article/7dfc66de-4d6d-11ed-af60-3f894fe60060 2/2 @RobertJenrick #Forgotten500k

Page 2 of The Times today is also leading with the Evusheld scandal. This is SUCH an easy win for the government to reverse. @RobertJenrick #Forgotten500k

Meanwhile, we've been on the BBC this morning!
We should be on BBC Radio Scotland at lunchtime, South Today & South East Today, Inside Health on Radio 4 on Tuesday, and Newsnight on Friday.
Covid: Time running out to protect vulnerable
https://www.bbc.co.uk/news/health-63254155
#Forgotten500k
BIG news as we unveil the campaign we've been working on with our charity partners for months: #Forgotten500k in support of @evusheld4theuk.
It starts with full-page national press adverts that will continue to run this week. Here's The Guardian.
https://getevusheld.uk/500k/ 🧵 1/8
We should be on BBC Breakfast this AM, too, BBC Radio Scotland at lunch time, South Today and South East Today, Inside Health on Radio 4 on Tuesday, and Newsnight on Friday. 2/8
These ads highlight the plight of the forgotten 500k immunocompromised individuals in the UK who are denied Evusheld by UK government policy. The advertising was designed pro bono by The&Partnership with media secured by mSix&Partners. They have been SO generous. 3/8
The #Forgotten500k campaign is set to run and run. We hope this is a show of power to the government, demonstrating that we will not go away! (Even if the government does 😬.) 4/8
We have a podcast from Andy Coulson’s “Crisis What Crisis?” series, a silent vigil in Parliament Square, a digital ad van circling Westminster, a Tortoise Media “Think In” event and the delivery of a letter personally by the group and charities to Number 10 Downing Street. 5/8
The goal of the campaign is to get the government to change its course on Evusheld. We have written to the Secretary of State for Health, @theresecoffey, the Health Minister, @RobertJenrick, and the Chancellor @jeremy_hunt. #Forgotten500k 6/8
The campaign has its own Facebook page to tell people new to the issue about Evusheld and it will be updated with new stories and adverts. Please do LIKE the page to help its organic growth: https://www.facebook.com/forgotten500k 7/8
Finally, the campaign site! None of this would be possible w/out the support from our charities & the pro bono media specialists.
Now, @RobertJenrick @theresecoffey: PLEASE give me the ability to safely hold my newborn nieces.
Please order Evusheld.
https://getevusheld.uk/500k/ 8/8








If Truss goes it will extend the already months and months and months of there basically being no government. Nothing is getting done, nobody is taking any long-term ministerial responsibility, and they are managing to trash the country.
Leadership contest, recess, conference season, another leadership contest? The soap opera of personality cult politics superseding everything else.
"Reference tables might not seem sexy".
Metadata always gets such a bad rap!
https://www.thedailybeast.com/eusebius-of-caesarea-was-the-mysterious-fifth-evangelist-who-created-the-bible-as-we-know-it
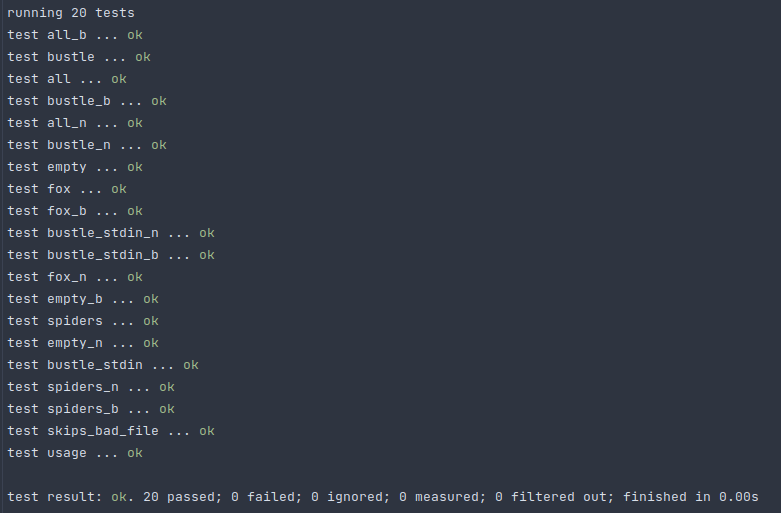
One of the things I really like about this book is its "challenge" nature. The author gives you the tests for the project and you then implement the code that satisfies them.
YEAH!

"in particular, individuals receiving immunosuppressants remained at high risk despite the initial booster"
Severe COVID-19 outcomes after full vaccination of primary schedule and initial boosters - The Lancet
https://www.thelancet.com/journals/lancet/article/PIIS0140-6736(22)01656-7/fulltext#%20
Day 2 of learning Rust and I'm going to re-write the GNU concatenation tool, cat.
Like many new Rustaceans, I imagine, I just got very excited about clap's automatic CLI parser
I mean, you just define the configuration for the app and tell it to parse and it creates the struct. :O
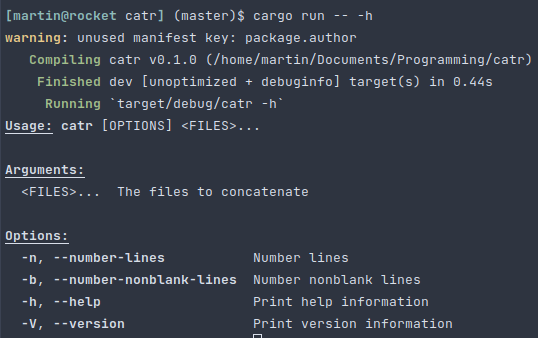
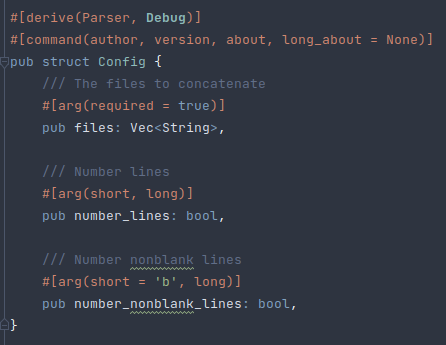
A brilliant piece today in the Scottish Herald on Sunday covering the Evusheld scandal. Though I am laughing at how much @MarkOak04974342 looks as though he's been pixellated out of 1992's Wolfenstein 3D or something...


A "BK nephropathy" sounds like the latest mega-offering from some fast-food joint. The only question is whether it comes with fries.

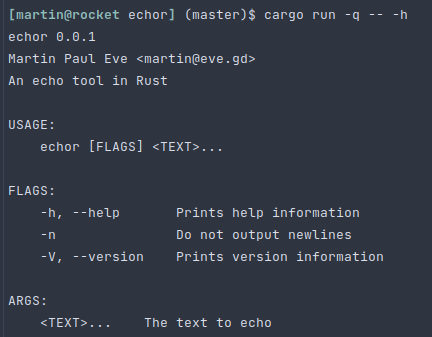
Meanwhile, I wrote my first, very basic, program in Rust. It's a clone of the "echo" tool. https://github.com/MartinPaulEve/echor
I admire my Twitter feed's collective determination to help me find a solution to my messy office that revolves around changing the tech stack, rather than clearing up.
OK, the old webcam had totally died and the replacement arrived today. It has a much wider field of vision, which means I'm going to need to do much more tidying...

That's my weekend sorted, mind.

Well, urgent call from renal confirmed the earlier news. BK Virus (I think of it as "bastard kidney virus") destroying my kidneys. Apparently there's an antiviral agent... But I can't have it, because it's nephro-toxic. So we're going for the IVIG plan and off my other treatment.
Spoke to the hospital...
They seem to have confirmed the virus as the cause of the kidney damage. They may need to take me off the drugs that control my arthritis as part of the treatment for this, although she said that this would "make me very ill". Great!
They have also found a very large inflammatory arthritic attack ongoing in my hip. This is why I have been unable to walk any distance on it for a year or so now. This must be treated with a direct guided deep steroid injection.
Every year this preservation manifesto comes around on my Facebook "memories" feed.

A teaser trailer for Andy Coulson's "Crisis? What Crisis?" podcast next week. I'll keep schtum until then but "after 50 episodes of this podcast, I've just recorded one that has left me slightly stunned"...
Generating this evidence is also challenging since the whole process would also be massively unethical! https://x.com/drlennardlee/status/1580403875806253056
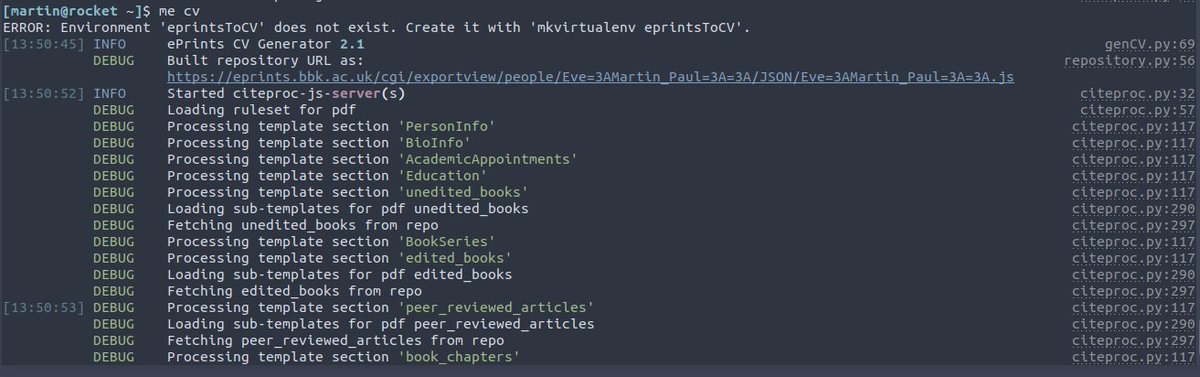
Debugging why an item from BIROn wasn't automatically being added to my CV (turns out I just hadn't specified that it was peer reviewed) and took the opportunity to upgrade my academic CV generator to use Rich logging.
https://github.com/MartinPaulEve/eprintsToCV
Virtual meeting this afternoon with one of our visiting researchers from Seoul. Interesting discussion of national academic publishing cultures and understanding commonalities in economics and funding. https://orcid.org/0000-0002-6007-316X
Ah yes. How can Imperial improve its reputation? Affiliation with a cryptocurrency exchange that's just been accused of misfiling its UK tax report 😬 https://news.bloombergtax.com/daily-tax-report-international/binance-filed-inaccurate-uk-accounts-says-joint-venture-partner

SOMEONE ON THE INTERNET IS WRONG

Someone's had a hard day, it seems...

The transcript of @libdemdaisy's Evusheld debate is now available on Hansard. She was extremely impressive and we're so grateful for her support. https://hansard.parliament.uk/commons/2022-10-12/debates/7D01C208-3A36-4F27-A7CE-E95C7F9DAB9F/ProcurementOfEvusheld
Evusheld Rejection 'Indefensible' as Calls Renewed to Approve COVID Treatment
https://www.medscape.co.uk/viewarticle/evusheld-rejection-indefensible-calls-renewed-approve-covid-2022a100246a
The continuing worst part of these high-dose corticosteroids (not the body-building kind!) is feeling as though your whole body is shaking inside. I'm tapering down the dose but you can't do this too quickly or you have an adrenal crisis and die.
Excited to see The Bloomsbury Handbook of Digital Humanities coming to fruition in 2023. Thanks to Bloomsbury for allowing zero-embargo deposit of the version of record of my chapter on day of publication, which I will do on launch. https://eprints.bbk.ac.uk/id/eprint/40856/
The UK's department for health and preprints.
Thanks to @Overtonio for getting in touch and showing me which UK governmental departments have been using medRxiv
https://eve.gd/2022/10/12/the-uks-department-for-health-and-preprints/
Ooh, I know this one! It's "don't have a pension in the UK because it will be worthless by the weekend due to government policy".
My webcam stopped working yesterday. Assumed it was some kernel update that was blocking it. Spent ages debugging. Eventually whacked it a couple of times. Works again now.
This afternoon's listening while admin-ining is Tracks and Traps by The Holy Fix. Slow chugging dark instrumental electronic.
trax...


A friend sent me this. Someone really should have caught it, of course, and it's funny.
But it's also easy to scoff. The people who typeset academic articles are not specialists. They may not even speak the language they are typesetting.
That's a function of market greed for profit combined with austerity drive on costs, seeking the cheapest labor without QA checks.

Whenever I see this, I then think: "and people want to base usage metric reports to libraries on this kind of geolocation approach...?" https://x.com/rmounce/status/1579803305907081217
"She’s also furious about the Government’s disinterest in antibody therapeutics." https://www.telegraph.co.uk/global-health/science-and-disease/dame-kate-bingham-rishi-sunak-didnt-even-know-what-vaccine-taskforce/
Even if you are not someone who would benefit from Evusheld, the government's decision-making process here should alarm you. From what the DHSC has published, just 4 people, with little expertise in the area, have blocked the treatment of 500k people. A brief thread 🧵 1/8
The DHSC "report" is here. The first thing to say is that this is pretty weak. It's just a summary of the papers and says "the quality of the data is insufficient". This is so flimsy that we can barely challenge it. 2/8 https://www.gov.uk/government/publications/rapid-c-19-oversight-group-report-to-chief-medical-officer-review-of-evusheld/rapid-c-19-oversight-group-report-to-chief-medical-officer-summary
But these doctors are NOT immune specialists. One is a neurosurgeon and the other a cardiologist. When @drlennardlee asked 125 experts from across 17 specialities what THEY thought, they were in favour of the drug. 4/8 https://getevusheld.uk/assets/downloads/consensusstatement.pdf
In this report, we're told that the appraisal was made by "senior members of RAPID C-19". Four people are listed: James Palmer, Helen Knight, Daniel McAuley, and Krishna Prasad. Only 2 of these are doctors: James Palmer and Krishna Prasad. 3/8
It's also a slap in the face to the group that was asked to decide who should get this drug. In May, a group of experts was asked to work out who should be given Evusheld. They did as asked and published the list. What a waste of their time. 6/8 https://www.gov.uk/government/publications/higher-risk-patients-eligible-for-covid-19-treatments-independent-advisory-group-report/defining-the-highest-risk-clinical-subgroups-upon-community-infection-with-sars-cov-2-when-considering-the-use-of-neutralising-monoclonal-antibodies
So what has happened here? Can this possibly be quorum for this group? What about external advisory boards? The fate of 500,000 people has been decided by 4 people, only 2 of whom are doctors, and they aren't specialists in immune compromise. 5/8
But in this case, they've gone for the worst of all worlds. They've given us a process that is opaque and autocratic, but that has delivered just delay after delay, while the deaths stack up. 8/8
The whole thing has an aura of unfair process. Yes, we want reactive, fast decision-making in a pandemic and that can mean using exceptional routes. 7/8

An article in the BMJ with substantial comment from me on behalf of @evusheld4theuk
Evusheld: Government is urged to expedite covid antibody treatment for vulnerable patients
https://www.bmj.com/content/379/bmj.o2431
We just met the government’s R&D spending target… or did we? | Wonkhe
https://wonkhe.com/blogs/we-just-met-the-governments-rd-spending-target-or-did-we/
It's as though they're marketing the Thomas Pynchon range directly to me!
Other items in the range include Sun Bloch for @the_blochian

Interview with Leftfield about the new album - the highlights for me are the return of Earl Sixteen and Lemn Sissay. The former on Leftism's "Release the Pressure" is truly superb.
https://www.theguardian.com/music/2022/oct/10/leftfield-band-music-neil-barnes-interview-this-is-what-we-do?CMP=Share_AndroidApp_Other
One of our charity partners, Blood Cancer UK, has responded to the wholly inadequate reply from the DHSC on Evusheld. They here tackle the issues of real-world evidence, lab-based testing, peer-review, and eligibility. The full letter is on our website: https://getevusheld.uk/assets/downloads/2022-10-04-Letter-to-Coffey.pdf



Today I read Percival Everett's I AM NOT SIDNEY POITIER. Totally over the top metafiction - amusing with some great stylistic parodies.

The NICE appraisal is, in our view, a flawed process that is delaying access to Evusheld. We are nonetheless engaging with it as a last resort while the campaign continues. You can read our submission on the documents, media, and research page. https://getevusheld.uk/4_media.html
Another week, another set of desperate messages.
"I locked down 2 March 2020 & have been shielding for 2 years, 7 months. I have no quality of life, live in constant fear, and am desperate to receive AstraZeneca's Evusheld. It is my only hope for anything like a normal future."
Just seen that Bruno Latour has died; a significant and controversial figure, of course.
Here's the chapter he wrote for our recent book: "How Does a Format Make a Public?"
https://direct.mit.edu/books/book/4933/chapter/625159/How-Does-a-Format-Make-a-Public
Today is a combination of Evusheld campaign planning and programming work.
We are the country taking the energy crisis least seriously. Even Shell’s boss is baffled
https://www.theguardian.com/commentisfree/2022/oct/09/we-are-country-taking-energy-crisis-least-seriously-even-shell-boss-baffled?CMP=Share_AndroidApp_Other
The conclusion here is WAY too optimistic
Advice is now "people who feel unwell should avoid vulnerable [people]". But you can't see who's vulnerable and "feeling unwell" is not a good measure of infectivity.
Also, vulnerable urged to avoid those who have Covid. But we can't see this either.
https://www.bbc.co.uk/news/health-63170006
Went to do the peer review. Author revealed who they are in a footnote, scuppering anonymity. Great work.
Now on to some weekend coding fun while jamming to some fine stuff from the tici taci back catalogue...
https://soundcloud.com/ticitaci/shunt-voltage-scapeism-clip
The DHSC's poor response to the letters I drafted. Now in @theresecoffey's hands. This advice goes directly against international clinical consensus. The people consulted have no immunology backgrounds, as opposed to the 125 clinicians who support its use: https://getevusheld.uk/assets/downloads/consensusstatement.pdf https://x.com/SGriffin_Lab/status/1578507542891999232
woodrush/lambda-8cc: x86 C compiler written in untyped lambda calculus
https://github.com/woodrush/lambda-8cc#running-times-and-memory-usage
Ah yes, I've found my teaching space!
* not my actual teaching space - a room in the hospital!

Going well this.


Today's work while hospital prod me is reading PhD student writing and a peer review for a journal article. I also have another Percival Everett novel with me as a treat if I get through the rest.
I always despair a bit when companies and customers in the "smart home" space get into fights over subscriptions. It usually runs like this: company sells you a piece of kit. You buy. Company then introduces a monthly or yearly subscription. Customers get very angry.
The challenge with this is that the company should have been honest about this cost upfront and not introduced it as an afterthought. That's clear. But there's a bigger question about sustainability here. Many object _in principle_ to an ongoing sub. I think that's wrong.
If there are ongoing costs to running a service - like a central server & giving ongoing tech support - then the revenue stream needs also to be continuous. One-time purchases can only sustain such a business by always selling more to new customers. Essentially a pyramid scheme.
I really want my smart home tech to be supported and continue to function, so I think I embrace subscriptions as a way of ensuring that. It's in my self interest to see such services continue.
Of course the best solution would also be that all smart home tech should come with the server-side components, so that if an org folds, the gear can be run off a home server by the technically competent. This would be such a strong pact from tech companies if implemented.
You might see independent service providers starting businesses off this, too. Supporting technologies abandoned by the original owners. I think fear that this might destabilise the original companies, running on subs, could be a factor inhibiting it.
Friday! Hurrah!
Off to hospital for more investigation of this BK Virus that's destroying my kidneys. Boo!
Apparently named for the initials of the index case/patient zero.
Article in The Lancet shows continued efficacy of Evusheld.
Yet Evusheld and "effective monoclonals are available but not offered to extremely clinically vulnerable patients with COVID-19 who are at risk of progressing to severe disease."
https://www.thelancet.com/journals/lancet/article/PIIS0140-6736(22)01938-9/fulltext
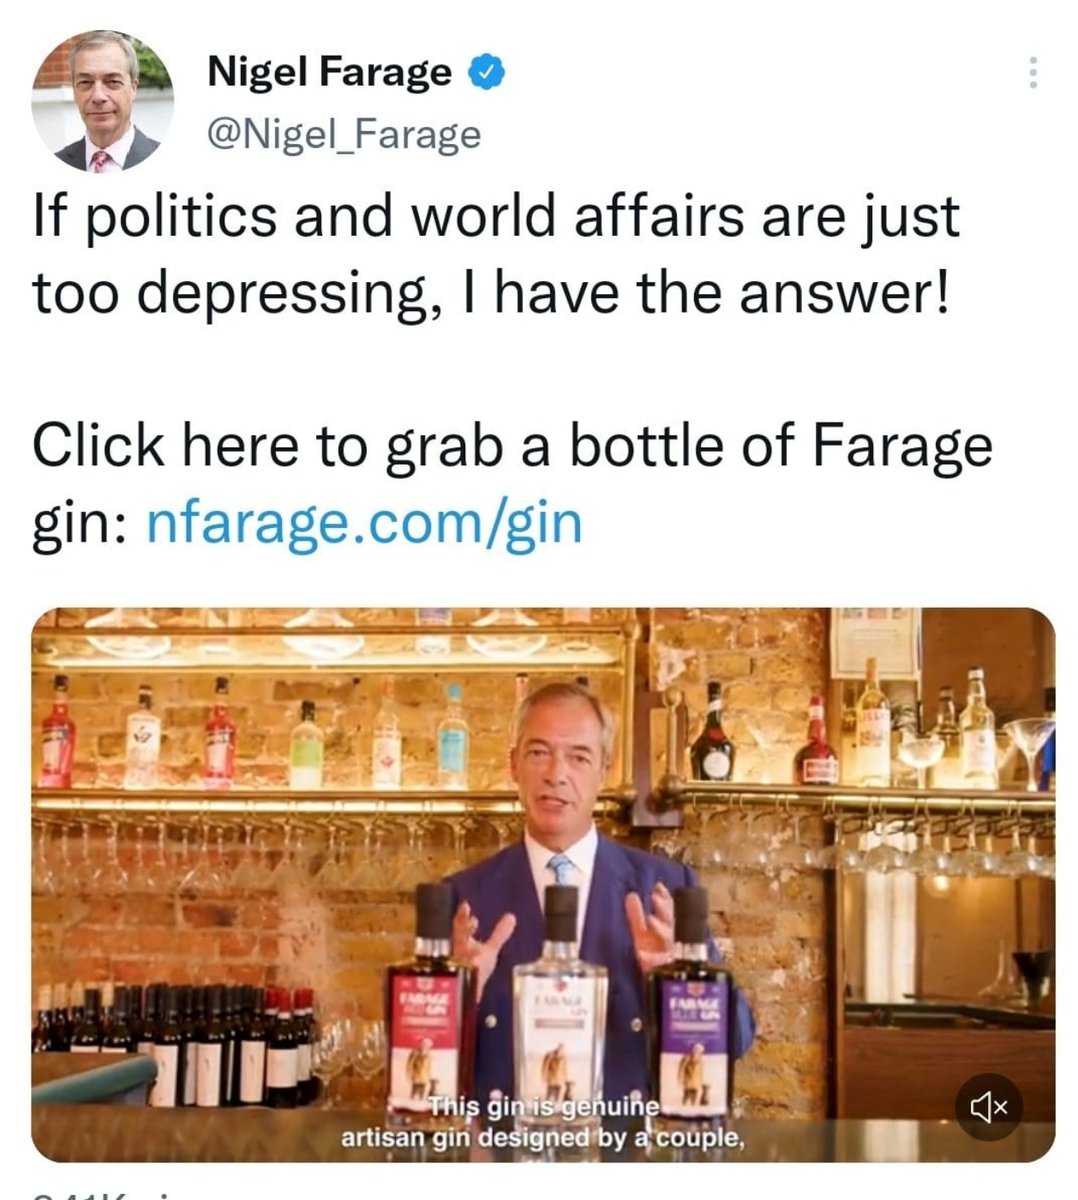
You've got to* admire the grift of spending 20 years laying the groundwork and making world affairs so grim that you need F*rage Gin.
* not in the slightest
I salute my forebears who broached this important question

In memory of pioneering @BirkbeckUoL computer scientist Kathleen Booth, who created assembly language while working at the university. http://blogs.bbk.ac.uk/bbkcomments/2022/10/06/remembering-professor-kathleen-booth-1922-2022/
Scotland's "Beyond Level 0" on Covid stuff sounds like a joke from Kung Fu Panda

Everybody who uses it seems to love the programming language Rust. I glance at the initial syntax and it looks horrific. I suppose I should learn its basics though.
Today's new book purchase is Matt Rubery's interesting sounding Reader's Block: A History of Reading Differences. Looking forward to this! https://www.sup.org/books/title/?id=34988
Silly little doggy


Hans Niemann probably cheated in more than 100 chess games, investigation finds https://www.theguardian.com/sport/2022/oct/04/hans-niemann-chess-com-cheating-investigation-magnus-carlsen
Don't stop me now, I'm having such a good time...
You can "stop me now" on this one


"Things... can only get better" https://x.com/ChrisMasonBBC/status/1577561847913381888
Morning research writing vibe

Protections against Toby's old-age accidents have now reached Patrick Bateman-esque murder-den territory.

Reading more of @bourke_joanna's history of Birkbeck this evening and the role that the institution played in the Lanchester kidnapping. A really interesting chapter on "The New Woman".
https://en.wikipedia.org/wiki/Edith_Lanchester
When immunology meets the pandemic, you get articles mentioning CVID (Common Variable Immunodeficiency) that just look like bad proofreading. (Which is a dying rat.)
"Fictional technology that nobody has yet got to work to be built in Nottingham"
https://www.itv.com/news/calendar/2022-10-03/worlds-first-nuclear-fusion-power-plant-to-be-built-in-north-nottinghamshire
I'm in the final stages of book writing (on the histories and philosophies of metaphor in digital text environments) and looking for people who might be willing to read and give critical feedback on chapters. Would paying £250 for a chapter (8k-12k words) be fair?
I'm just trying to come up with a fair figure here -- and that's more than you get for peer reviewing a whole manuscript in my experience in the academic book world.
Feedback

Simba did not spark joy

"Authors might fear... that other researchers will use the raw data to make fresh discoveries"
Heaven forbid that someone else finds something good and of benefit to the world in your data!
https://www.nature.com/articles/d41586-022-03133-5
Today was 4.5 hours of credit card receipt classification/upload, 2 hours of email, and 1.5 hours of planning meetings. And 45 mins of hospital fun. Admin heavy and hoping for greater diversity for the rest of the week!
I just spoke with the renal team at the hospital.
First, my current level of kidney function is ~27%. So it’s not great, but also not terrible enough to require dialysis yet. It seems to have been slowly getting worse over a relatively long period.
Second, and here's where it gets weird and problematic, they have identified the problem, but it’s also not very good. Apparently I have signs of a “BK Virus” that I am unable to clear because of my immunosuppression.
They have never seen this before in a native (as opposed to transplanted) kidney, although it’s common (and problematic) in transplant patients. I have to go in for lots of further tests now.
They then they want to give me high-dose intravenous immunoglobulin to try to evict the virus using conferred immunity. However, this is not a standard protocol. But it does make sense.
https://x.com/trussliz/status/1576827031194865664

While a recent in-vitro study showed reduced antibody neutralization of Tix-Cil against Omicron variants, this did not have a significant clinical outcome in our study or similar studies during the Omicron variant period https://www.amjmed.com/article/S0002-9343(22)00637-4/fulltext
Today's a day of writing, then tidying/cleaning, then programming, then Skypeing with friends.
I'm also enviously eyeing up more powerful GPUs and thinking "then I could train myself into Stable Diffusion".
Must. Stop. Looking.
Bereaved families fear Covid inquiry cover-up after ban on testimony.
These are the families of people who were given totally inappropriate blanket "do not resuscitate" orders.
https://www.theguardian.com/uk-news/2022/oct/02/bereaved-families-fear-covid-inquiry-cover-up-after-ban-on-testimony?CMP=Share_AndroidApp_Other
Rust Infrastructure Pull Request Submitted For Linux 6.1.
Remarkable to see this make it through. Could have such great memory safety implications for the kernel.
https://www.phoronix.com/news/Rust-For-Linux-6.1-Pull-Request
The Musk robot even looks like The Terminator. https://x.com/AlexBlechman/status/1457842724128833538
Hindawi and Wiley to retract over 500 papers linked to peer review rings
https://retractionwatch.com/2022/09/28/exclusive-hindawi-and-wiley-to-retract-over-500-papers-linked-to-peer-review-rings/
The project that literally nobody needed or wanted 😂 https://x.com/RetroTechDreams/status/1576015554586251264
Recent hospital was one of those weird cases that seem antithetical to medicine, but is actually quite common. I went in feeling OKish. Unwell, but no more so than usual(!) Blood tests showed a problem, so they put me on high-dose steroids and I now feel much worse.
The invisibility of many illnesses/problems, except to microscopic blood tests, and the false assumption that medical interventions are always concerned with "making you *feel* better" makes for a curious medical environment.
The Pandemic’s Legacy Is Already Clear.
All of this will happen again.
https://www.theatlantic.com/health/archive/2022/09/covid-pandemic-exposes-americas-failing-systems-future-epidemics/671608/
Really geeky thing to get excited about, but my new mouse arrived. A Logitech MX Vertical wireless. Moving to a vertical mouse was the single biggest ergonomic improvement that I've made in recent years. Truly recommend it for those who work long hours on a computer.
The other great one is the Microsoft Sculpt keyboard. This takes way more getting used to than the mouse, but the tenting and hand angle, again, do wonders for reducing RSI injury. Highly recommended.


Explicitly clarifying that your robot will "not overpower humans" will definitely reassure people. https://x.com/washingtonpost/status/1575879429427023874
Professor Kerr - an oncology specialist at Oxford - is right. Government needs to intervene to get access to this drug for the winter, right now. It would save lives. The number of voices saying this is only growing. https://x.com/RadarsTrend/status/1575737746773229568